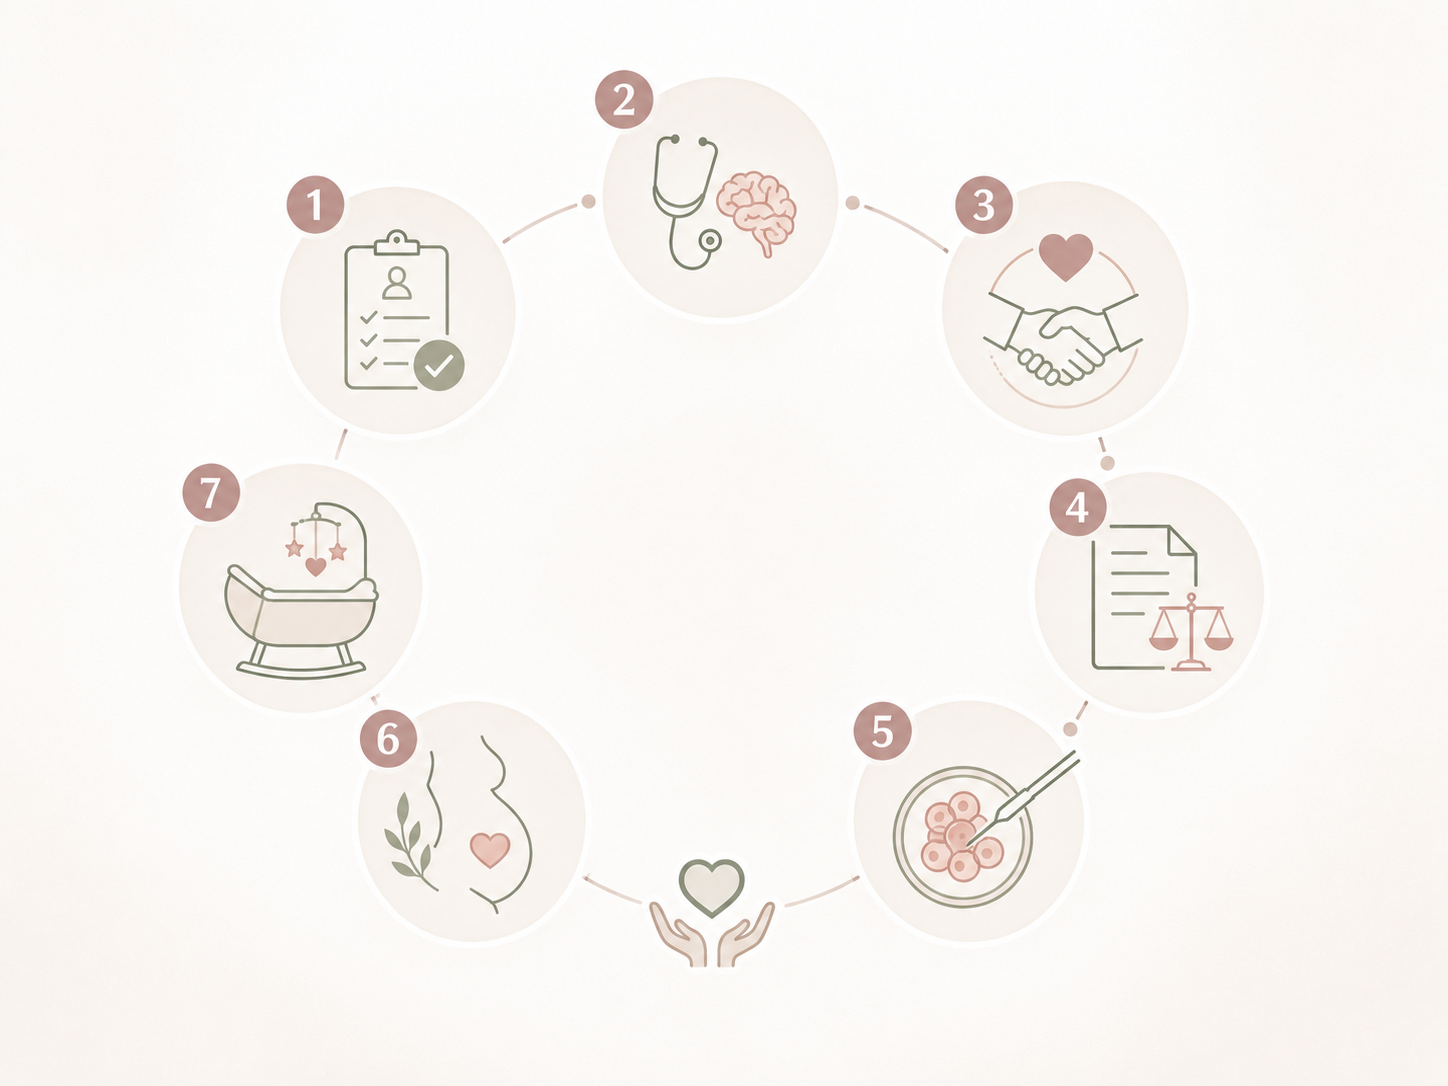
A surrogacy journey has one stage with a knowable length and several with none. The pregnancy is the knowable one: once a day-5 embryo is transferred, the American College of Obstetricians and Gynecologists puts the estimated due date at 261 days from the transfer date, which is a little under nine months. Everything before the transfer runs on human and legal time rather than clinical time, and that is where journeys actually differ from one another. So the more useful question than "how long does surrogacy take" is "which stage am I in, and what has to close before the next one can open." This page answers that stage by stage, and it is honest about which durations are documented and which are not.
What are the stages of the surrogacy process, and how long does each one take?
A gestational surrogacy journey moves through roughly ten stages. Some have durations you can look up in a professional guideline or a peer-reviewed dataset. Several have no published duration at all.
- Creating and testing embryos - Partly · Ovarian stimulation for the person providing eggs typically runs 8 to 14 days, and eggs are retrieved about 36 hours after the trigger injection (ASRM). When embryos are genetically tested, results typically come back 1 to 2 weeks after biopsy and the embryos are frozen while the lab works (Washington University Fertility Center). · Whether embryos already exist, whether a donor is needed, and whether genetic testing is done.
- Matching with a gestational carrier - No · No professional body or public dataset publishes a match wait. · Medical criteria, carrier availability, and what both sides want from the relationship.
- Screening the carrier - No duration, but there are published expiry rules · ASRM specifies the medical, infectious disease, and psychological screening, and states that a psychological evaluation conducted more than a year before a new contract must be done again (ASRM, 2022). · How quickly appointments and records come together, and whether a finding requires treatment and a retest.
- Screening the intended parents - No · Laws and guidelines generally require each intended parent to complete a mental health evaluation and a background check, and to have independent legal representation before an agreement can be executed. Connecticut writes this into statute (Conn. Gen. Stat. 46b-522). · State law and scheduling.
- The legal agreement - No duration, but it is a hard gate · A fully executed agreement and a legal clearance letter must be in place before treatment begins and no later than the start of the IVF cycle (ASRM, 2022). California bars the transfer, and even the injectable medication that precedes it, until the agreement is fully executed (Cal. Fam. Code 7962(d)). · Negotiation, the state, and how quickly both attorneys move.
- The carrier's preparation cycle - Partly · In a hormone-prepared frozen transfer, estrogen priming can run from roughly a week to as long as four weeks without reducing live birth rates, and progesterone is generally started about six or seven days before a blastocyst transfer (Reprod Biol Endocrinol, 2023). · Clinic protocol and calendar.
- Waiting to learn whether the transfer worked - Set by the clinic, not by a guideline · Clinics assign a fixed test date and ask patients not to test before it (Guy's and St Thomas' NHS Foundation Trust). · The embryo's stage and the clinic's protocol.
- A second transfer, if one is needed - Not a duration, but may be necessary · 54.3% of embryo transfers to a gestational carrier resulted in a live birth, across 40,177 gestational carrier cycles from 2014 to 2020 (JAMA, 2023). · Whether frozen embryos remain available, and the clinic's review after a negative result.
- Pregnancy - Yes, and precisely · For a day-5 embryo the estimated due date is 261 days from the transfer date (ACOG Committee Opinion 700). Full term is 39 0/7 through 40 6/7 weeks (ACOG Committee Opinion 579). · Delivery before term. In the JAMA cohort, 73.2% of gestational carrier live births were term, 23.2% preterm, and 3.6% very preterm.
- Legal parentage - Depends on the state, and it can begin early · In Connecticut a parentage proceeding may be initiated at any time after all parties execute the agreement, and the judgment may issue before birth and take effect immediately upon the birth of the Child with enforcement stayed until the child is born (Conn. Gen. Stat. 46b-531). · The state where the child will be born.
For the full description of what happens inside each stage, rather than how long it takes, read the surrogacy process from start to finish.
Why do published surrogacy timelines disagree with each other?
Because almost none of them come from a source that measures anything. Search "how long does surrogacy take" and you will find ranges that do not match each other: most often, matching times vary. Note that any reputable surrogacy agency will have a waiting time for a match with a surrogate. Why? One, because these agencies have parents waiting. They have parents waiting because they are good at what they do and intended parents choose agencies where reviews are good, and the team is experienced and has the resources to support each surrogacy journey it is matching. Two, because it is very restrictive for a woman to become a surrogate and only approximately 5% of surrogate applicants are successful in passing all screening.
No total journey length appears in the published guidance of the American Society for Reproductive Medicine, the American College of Obstetricians and Gynecologists, or the Society for Assisted Reproductive Technology. Those bodies publish a great deal about how each step must be performed, in what order, and to what standard. None of them puts a number on the whole. That absence is meaningful rather than an oversight: total journey length is not a clinical quantity, it is the sum of one medical timeline and several administrative and human ones.
The practical consequence for an intended parent is this. Treat any single headline range as a planning assumption rather than a fact, and ask an agency instead for the two things that are actually answerable: what its own recent journeys have looked like, and what the gate is at the end of the stage you are in.
How long does it take to get matched with a surrogate?
There is no credible published answer across the field, but Worldwide Surrogacy will give you an estimate of matching time and it is currently 8 to 10 months. An agency that gives you a firm number is describing its own caseload, and so is this one - it moves with how many surrogates are completing screening at any given time. The reason is that, in addition to a match being a queue position, it is also a mutual decision between an intended parent and a woman who is choosing whom to carry for, and both sides have criteria.
What can be said with evidence is that demand for gestational carriers grew substantially in the years before the most recent national data. Cycles using a gestational carrier rose from 3,538 in 2014, which was 2.7% of all embryo transfer cycles, to 8,145 in 2019, which was 5.2%, before easing to 6,909 in 2020 (JAMA, 2023). More than a doubling in five years, against a pool of women who must first meet a demanding medical profile, is the structural reason matching takes time.
Two things genuinely shorten it, and neither is urgency. The first is flexibility on criteria that are preference rather than medicine. The second is being ready on the other side of the match, which for most families means having embryos already created and frozen. What matching actually involves, and how a match is built rather than assigned, is covered on how matching works.
How long does surrogate screening take, and can screening expire?
Screening has no published duration, but it does have published expiry rules, and those matter more to your timeline than the appointments themselves. The American Society for Reproductive Medicine's 2022 guidance for practices using gestational carriers sets out what screening covers: a medical history and physical examination, blood type, cervical cancer screening and mammography per ACOG guidance, varicella and rubella titers, a urine drug screen, a uterine cavity evaluation, a defined panel of infectious disease testing, and a psychological evaluation by a qualified mental health professional that includes standardized testing and a clinical interview (ASRM, 2022).
Two rules in that document are timeline rules rather than clinical ones. ASRM states that a psychological evaluation "should be administered any time a new surrogacy contract is initiated, and if an evaluation was conducted over a year before the new contract, a new evaluation should be conducted." It also sets narrow windows for laboratory testing around the retrieval, specifying testing "within 7 days of semen production and 30 days before or 7 days after oocyte acquisition." ASRM further notes that where an infection is found, the carrier "should be treated, retested, and deferred from use as a GC until after documentation that treatment was successful."
The practical translation is that a long pause between stages is not free. Screening results have a shelf life, and a journey that stalls for months can arrive at the transfer needing work already done to be done again. This is the strongest argument for keeping the legal and medical tracks moving in a coordinated sequence rather than letting one wait on the other.
The eligibility standards that screening measures against are the same ones ASRM names elsewhere: a carrier preferably between 21 and 45 years of age who has had at least one term, uncomplicated pregnancy, and who has not had more than five previous deliveries or three deliveries by cesarean section. ASRM sets the outer guidance; in practice most fertility clinics apply a tighter limit and cap a carrier's age at 41 or 42, so the clinic your carrier is treated at may be the narrower constraint.
Do intended parents get screened too?
Laws and Guidleines require that each intended parent, whether or not genetically related to the child, has attained 21 years of age, has completed a mental health evaluation by a licensed mental health professional, has undergone a background investigation, and has independent legal representation of the intended parent's choice, before a surrogacy agreement can be executed (Conn. Gen. Stat. 46b-522(b)).
That is a real appointment on your calendar, and because it is a condition of executing the agreement, it sits on the critical path rather than beside it. Requirements differ from state to state, so the question to ask early is not whether you will be screened but what your state requires of you specifically. Surrogacy law is set state by state with no overarching federal statute (ASRM, Gestational Carrier Policy in the United States), which is why this answer changes depending on where the agreement is executed and where the child will be born. See surrogacy law by state.
Do you need embryos before the journey can start?
For many surrogacy programs, you do not need embryos to sign on with the agency and begin the waiting time for a surrogate, but you must have embryos made before a match with a surrogate is made. In the most recent national data, 90.1% of embryo transfers to a gestational carrier used a frozen or thawed embryo rather than a fresh one, compared with 65.9% of transfers without a carrier, and 63.2% of gestational carrier cycles used preimplantation genetic testing (JAMA, 2023).
What that means in calendar terms is that the IVF stage and the transfer stage are usually two separate chapters, not one continuous block. Embryos are created, tested, and frozen on one clock, and the transfer happens on the carrier's clock later. Ovarian stimulation itself typically runs 8 to 14 days with retrieval about 36 hours after the trigger injection (ASRM), and where embryos are biopsied for genetic testing, results typically come back 1 to 2 weeks later while the embryos remain frozen in the laboratory (Washington University Fertility Center).
The consequence is straightforward. Families who arrive at matching with tested, frozen embryos have removed a whole chapter from their timeline. Families who still need to create embryos, and particularly those who will use an egg donor, should expect that work to sit ahead of the transfer rather than alongside it. How the medical side works in detail is covered on IVF and the medical process.
Why can't the legal contract be done at the same time as the medical steps?
Because professional guidance and, in several states, statute, forbid it. This is the part of a surrogacy timeline that people most often assume can be compressed, and it is the part that cannot.
The American Society for Reproductive Medicine states that before the initiation of any treatment, a fully executed legal agreement, a clearance letter attesting to the completion of that agreement, and all informed consent documents should be in place, and that "before medical treatment, and no later than the initiation of an in vitro fertilization cycle, legal counsel for the parties should present the ART practitioner with a legal clearance letter" (ASRM, 2022).
Two states write versions of that rule into their statute books, in stronger terms. California provides that the parties "shall not undergo an embryo transfer procedure, or commence injectable medication in preparation for an embryo transfer for assisted reproduction purposes, until the assisted reproduction agreement for gestational carriers has been fully executed" (Cal. Fam. Code 7962(d)). Connecticut requires that the agreement "shall be executed before a medical procedure occurs related to the surrogacy agreement, other than the medical and mental health evaluations," and separately requires that any compensation be "placed in an escrow account prior to the commencement of any medical procedure" (Conn. Gen. Stat. 46b-523).
Screening can begins before the contract. Medication cannot. Funding has to be in place before medication too. So the contract is not paperwork that trails the medical process; it is the gate the medical process waits behind, and the speed of the legal stage sets the start date of everything after it.
This is where the structure of an agency shows up in your calendar rather than in its marketing. Worldwide Surrogacy Specialists was founded and is led by a practicing reproductive attorney, which means legal expertise shapes how the agreement and the parentage work are structured from the start rather than being reviewed after the medical plan is set. Intended parents working with WSS also pay for the gestational carrier's independent attorney, which Connecticut separately requires of intended parents by statute, and journey funds are held through an independent third-party escrow arrangement rather than by the agency. What the contract itself covers is described on the legal side of surrogacy.
How long is the carrier's preparation cycle before the embryo transfer?
The medicated preparation cycle generally spans a few weeks, and the clinic has real latitude in how it is scheduled. In a hormone-prepared frozen embryo transfer, estrogen is given to build the uterine lining and progesterone is added to make it receptive. A 2023 review of clinical practice in *Reproductive Biology and Endocrinology* reports that as little as 5 to 7 days of estrogen may suffice for adequate priming, that estrogen treatment "can be as long as 4 weeks without a negative impact on the LBR," meaning the live birth rate, and that for a frozen blastocyst, transfer on the sixth or seventh day of progesterone administration is preferable to the fifth (Zhang et al., 2023).
The useful point for planning is that this stage is flexible by design. The clinic can start it when the calendar allows, which is precisely why it usually waits for the legal clearance described above rather than the other way around.
How long after the embryo transfer do you find out if it worked?
Your clinic sets a fixed test date, generally a little under two weeks after the transfer, and asks that no one test earlier. The exact day depends on the stage of the embryo transferred and on the clinic's own protocol. One NHS fertility service, for example, transfers embryos 2, 3, or 5 days after fertilization and sets the pregnancy test at 16 days after egg collection, with the instruction: "Please do not take the pregnancy test earlier than the date that we give you" (Guy's and St Thomas' NHS Foundation Trust).
The major reproductive medicine bodies do not publish a single standard interval, which is why the specific date should come from your carrier's clinic rather than from an article. Every US figure that circulates for this step traces back to an individual clinic's or agency's own page rather than to a guideline, so none is quoted here. What is consistent is that the confirmation is a clinic blood test rather than a home test, and that the wait is short in calendar terms and long in every other way.
What happens to the timeline if the first transfer does not work?
A second transfer is a normal branch of a surrogacy timeline rather than an exceptional one, and it is the largest single source of variation in journey length. In the most recent national analysis, 54.3% of embryo transfers to a gestational carrier resulted in a live birth, compared with 43.6% of transfers without a carrier, across 40,177 gestational carrier cycles between 2014 and 2020 (JAMA, 2023).
While there is a good change of achieving a pregnancy on the first transfer, planning as though the first transfer will certainly work is the most common way intended parents end up feeling that a journey has gone wrong when it has in fact gone normally.
In calendar terms, a repeat transfer adds another preparation cycle for the carrier plus the clinic's review of what happened, rather than a return to the beginning. Families who banked more than one tested embryo are in a materially better position here, because the alternative is returning to the IVF stage before the transfer stage can resume. What causes a transfer not to take, and what usually happens next, is covered in failed embryo transfers, now what.
How long is the pregnancy, and when do you know the due date?
The pregnancy is the one stage that arrives with a date on the calendar from day one, and in a surrogacy pregnancy that date is known more precisely than in almost any other pregnancy. Because conception happened in a laboratory on a known day, the due date is calculated from the embryo rather than estimated from a last menstrual period. ACOG, the American Institute of Ultrasound in Medicine, and the Society for Maternal-Fetal Medicine state that where a pregnancy resulted from assisted reproductive technology, "the ART-derived gestational age should be used to assign the estimated due date," and give the arithmetic directly: "for a day-5 embryo, the EDD would be 261 days from the embryo replacement date. Likewise, the EDD for a day-3 embryo would be 263 days from the embryo replacement date" (ACOG Committee Opinion 700).
261 days is roughly eight and a half months from the transfer. That is the longest single block in a surrogacy timeline, and it is set by biology rather than by anything an agency, a clinic, or a court can adjust.
Babies, of course, do not honor the arithmetic exactly. ACOG defines full term as 39 0/7 through 40 6/7 weeks of gestation, with early term at 37 0/7 through 38 6/7, late term at 41 0/7 through 41 6/7, and postterm at 42 0/7 and beyond (ACOG Committee Opinion 579). In the national gestational carrier data, 73.2% of live births were term deliveries, 23.2% were preterm, and 3.6% were very preterm, and 14.8% of those live births were twins or higher order multiples (JAMA, 2023). Planning for a delivery some weeks before the due date, particularly around travel and time away from work, is more realistic than planning for the date itself.
When do intended parents become the child's legal parents?
Most often, intended parents become the legal and custodial parents of their baby before the birth by way of a pre-birth court order that takes effect immediately upon the birth of the baby. There is no federal surrogacy statute, and states fall broadly into those that permit gestational carrier arrangements by statute, those with no statute or case law either way, and those that restrict or void such contracts (ASRM, Gestational Carrier Policy in the United States).
Where a state does permit a pre-birth parentage order, the timing is often generous. Connecticut provides that a party to a gestational surrogacy agreement "may initiate a proceeding for a judgment of parentage of a child conceived pursuant to the agreement at any time after the agreement has been executed by all of the parties," and that the court "may issue an order or judgment under this subsection before or after the date of birth of the child," while staying enforcement until the birth (Conn. Gen. Stat. 46b-531). California permits an action to establish the parent and child relationship to be "filed before the child's birth" (Cal. Fam. Code 7962(e)). Massachusetts permits a party to commence a parentage proceeding "before, on or after the birth of a child conceived by assisted reproduction under a gestational surrogacy agreement," and provides that a judgment issued before the birth "shall not take effect until the birth of the resulting child" (Mass. Gen. Laws c. 209C, s. 28I).
Pre-birth routes are not available everywhere, though, and the map is changing quickly. Both of the newest examples above are recent law: the Massachusetts Parentage Act was approved on August 8, 2024 and took effect on January 1, 2025 (Acts of 2024, chapter 166), and Michigan's Assisted Reproduction and Surrogacy Parentage Act, Public Act 24 of 2024, took effect on April 2, 2025 (Michigan Legislature). A state-law summary written even two years ago may now be out of date, which is a reason to confirm the current rule for your specific state with an attorney rather than rely on a general article, including this one.
The principle underneath all of it was settled in Connecticut in a case Worldwide Surrogacy Specialists' founder argued. In *Raftopol v. Ramey*, 299 Conn. 681 (2011), the Connecticut Supreme Court took up the question of "whether Connecticut law permits an intended parent who is neither the biological nor the adoptive parent of a child to become a legal parent of that child by means of a valid gestational agreement," and held that such a parent could, without adoption (CourtListener). Victoria Ferrara, the Founder of Worldwide Surrogacy, was lead counsel and argued the case before the court. How pre-birth parentage orders work in practice is covered on pre-birth parentage orders.
What makes a surrogacy timeline faster or slower?
Four things move a surrogacy timeline more than anything else, and they are not the four most people expect.
Whether you already have embryos. Because 90.1% of transfers to a gestational carrier used frozen embryos in the most recent national data, arriving at a match with tested embryos in storage removes a chapter from the front of the journey. Needing an egg donor adds one.
Whether the first transfer works. Where the embryos have been genetically tested, the first transfer carries a live birth rate of about 65%, and across up to three transfers fewer than 5% of patients fail to reach a clinical pregnancy (Pirtea et al., *Fertility and Sterility* 202100100-5/fulltext)). A second transfer may or may not be necessary but should not be unexpected, and having more than one embryo banked is what keeps that branch short.
How quickly the legal stage closes. Because the contract is a gate rather than a parallel task, every week the agreement is open is a week the medication cannot start.
Your matching criteria. Being open to the location of your surrogate, and being open to paying for health insurance for your surrogate, are two factors that can speed up the matching time.
Notably absent from that list is anything to do with pressing harder. Screening findings need treatment and retesting when they arise, matches are mutual decisions, and courts move at their own pace. What an agency can genuinely influence is sequencing, which is to say keeping the legal, medical, and financial tracks in the right order so that nothing waits on something that could have been done earlier, and so that no screening result expires while another stage catches up.
Frequently asked questions
How long does the whole surrogacy process take?
No professional body publishes a total, and it will most likely take approximately two years to have a baby through gestational surrogacy. The pregnancy alone accounts for roughly 261 days from a day-5 embryo transfer (ACOG Committee Opinion 700), and matching, screening, the legal agreement, and the carrier's preparation cycle all sit ahead of it. Nearly every range you see quoted comes from an agency or a fertility clinic describing its own caseload rather than from a dataset, so treat it as a planning assumption rather than a fact.
What is the longest stage of a surrogacy journey?
The pregnancy is the longest fixed stage at about eight and a half months from the transfer. Matching is usually the longest variable stage.
Can the legal contract and the medical steps happen at the same time?
No. ASRM's 2022 guidance requires a fully executed agreement and a legal clearance letter before treatment begins and no later than the start of the IVF cycle, and California statute bars even injectable medication before the agreement is fully executed (Cal. Fam. Code 7962(d)). Screening can run in parallel. Medication cannot.
How likely is it that the first embryo transfer works?
In the most recent national analysis, 54.3% of embryo transfers to a gestational carrier resulted in a live birth (JAMA, 2023). That figure covers every carrier transfer; where the embryos have been genetically tested the odds are better, with a live birth rate of roughly 65% on the first transfer and fewer than 5% of patients failing to reach a clinical pregnancy across three (Pirtea et al., *Fertility and Sterility* 202100100-5/fulltext)). A second transfer is a normal part of many journeys rather than a setback.
When do intended parents become the legal parents?
It depends on the state. Many states allow a parentage proceeding to begin before the birth, with the order taking effect at the birth.
Does having embryos already frozen make the process faster?
It removes the embryo creation chapter from the front of the timeline, which for many families is the single largest saving available. It also means a repeat transfer, if one is needed, does not send you back to an IVF cycle first. Another possibility is to engage a surrogacy agency to get on the matching list, and then create embryos while waiting for the matching time to pass.
Where to go next
The most useful thing to know about a surrogacy timeline is not its length but its order, because the order is what determines when each stage can start. If you are trying to work out what your own journey would realistically look like, a conversation about your specific situation will tell you more than any published range: whether you already have embryos, which state's law governs your agreement, and what has to close before the next stage opens.
At Worldwide Surrogacy Specialists, the same case manager stays with a family from the first conversation through delivery, so the sequencing described on this page is held by one person who knows where your journey stands rather than passed between departments. The agency was founded and is led by Victoria Ferrara, a reproductive attorney who has specialized in this area of law for over 25 years, which is why the legal stage that gates everything else is shaped by legal expertise from the start rather than reviewed at the end.

Article Categories